








01
Assess
We assess the foot as it loads, and measure the position of the first metatarsal and the big toe, rather than looking at the bump alone.
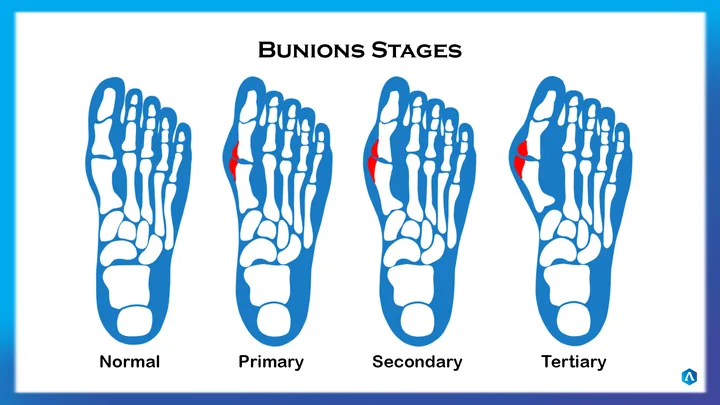
A bony bump at the base of the big toe, where the toe drifts across towards the others. Bunions form in stages, and what drives them is mechanical.
Trusted by patients from Sydney to Narrabri


If this sounds like your pain, there is a structural reason for it. The assessment is what finds it.
The first of the long bones behind the big toe is often naturally a little short, and sits angled in towards the middle of the body. For it to reach the ground, the foot rolls in. As it does, the ground pushes the big toe across and rotates it, and over time the muscles that pull the toe inwards shorten and hold it there. Where a bunion forms on one side only, a longer leg rolling in more than the other is often behind it.
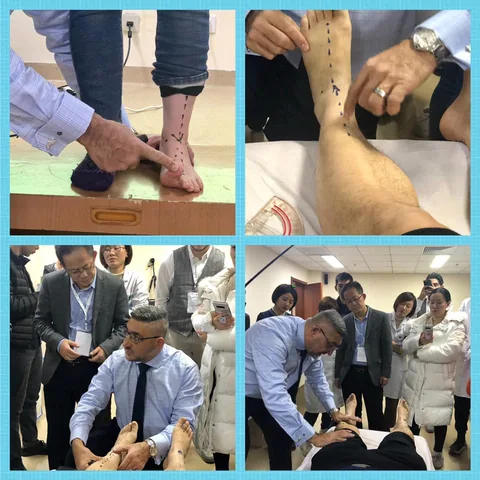
Bunions is diagnosed with the Najjarine Biomechanical Assessment, so treatment is prescribed against a finding rather than a symptom.
We assess the foot as it loads, and measure the position of the first metatarsal and the big toe, rather than looking at the bump alone.
We identify what is driving the toe across — foot alignment, a short first metatarsal, a leg length difference, or footwear — and explain what we found.
Treatment is aimed at that cause, because a bunion that is not addressed mechanically tends to keep progressing through its stages.
All ten treatments, starting with those most often used for bunions. Which you need is decided at the assessment; most plans combine more than one.
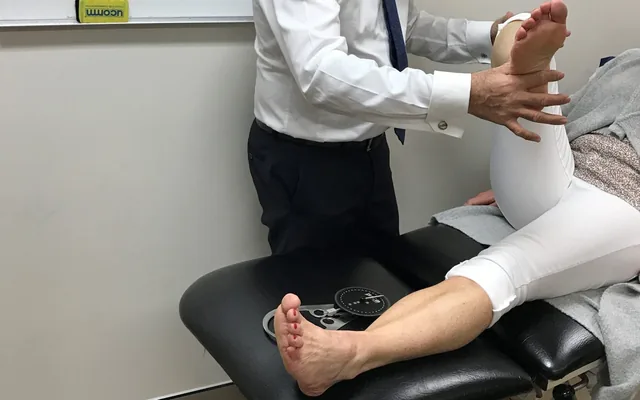
A full lower limb assessment from the feet up. It is the foundation of every treatment plan we prescribe.
Read more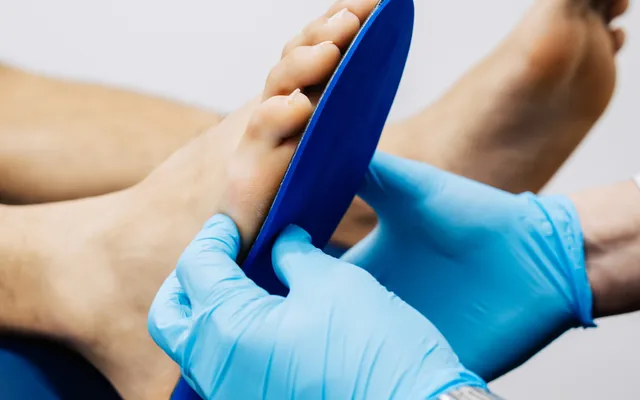
Prescribed devices that change how your foot meets the ground. Manufactured on site at our Kirrawee head office.
Read more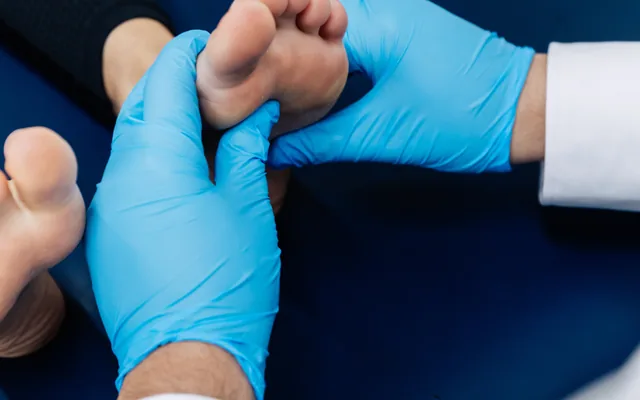
Hands-on work addressing restrictions across the foot’s 26 bones.
Read more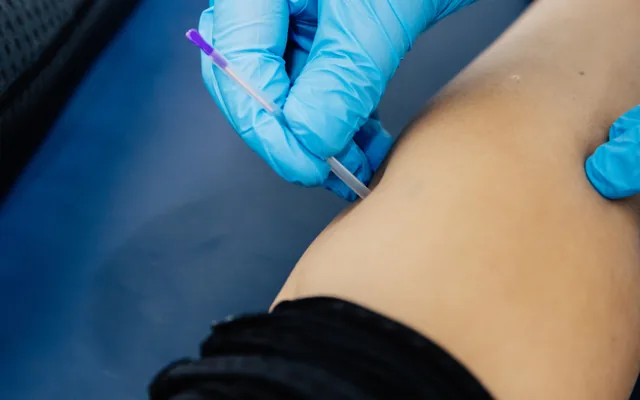
Fine needles inserted into trigger points to break down restrictive tissue.
Read more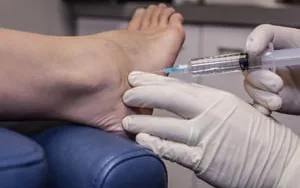
Injectable therapy to stimulate a repair response. Paired with prolotherapy.
Read more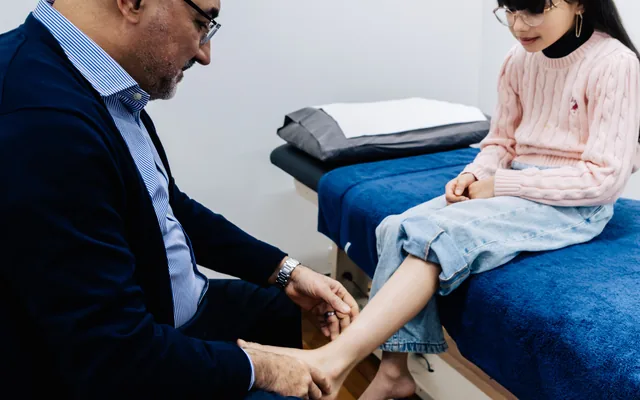
Pigeon toe, flat feet and growing pains, assessed while the foot is still developing.
Read more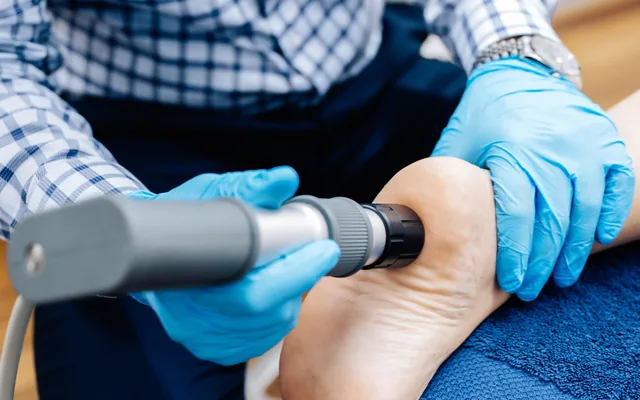
Acoustic waves using kinetic energy to stimulate repair in tendon and soft tissue. We use it most often for persistent heel pain and Achilles pain.
Read more
Running injuries, return to sport, and footwear that matches your gait.
Read more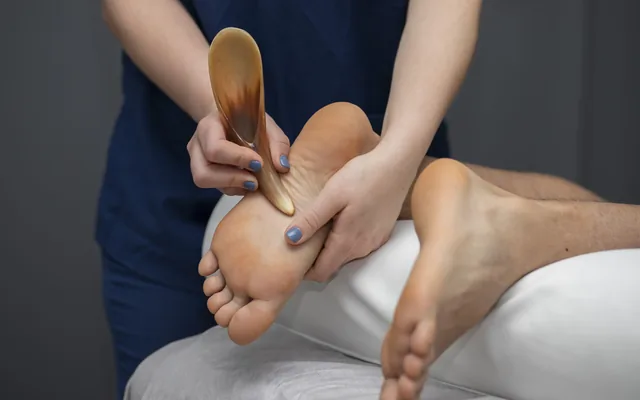
Routine care including ingrown toenails, corns and calluses.
Read more
Therapeutic support to offload tissue while it recovers.
Read moreEvery clinic books into its own diary. Choose the one nearest you.

First time anyone explained why it had formed rather than just pointing at the bump.
Had surgery years ago and it was coming back. Now I know why.
Clear about what orthotics would and would not do.
A night splint may ease the pain, but it will not correct the bunion. As soon as you walk again the mechanics that caused it are still there, and the drift continues.
Progression can usually be slowed where the cause is addressed early. By the later stages, once the joint has changed shape, the deviation itself is not reversible, which is why it is worth assessing before it gets there.
That is a decision for you and your surgeon. What we assess is the mechanical cause, which surgery does not change on its own.
Surgery corrects the toe; it does not correct the way the foot loads. Where that is left unaddressed, the bunion can return over the years that follow.
A one-sided bunion often points to a leg length difference, where the longer leg rolls in further. That is one of the things the assessment measures.
No. You can book directly.
Treating lower limb pain since 1990
Choose your clinic and book straight into its diary, or call and we will point you to the right practitioner.
