

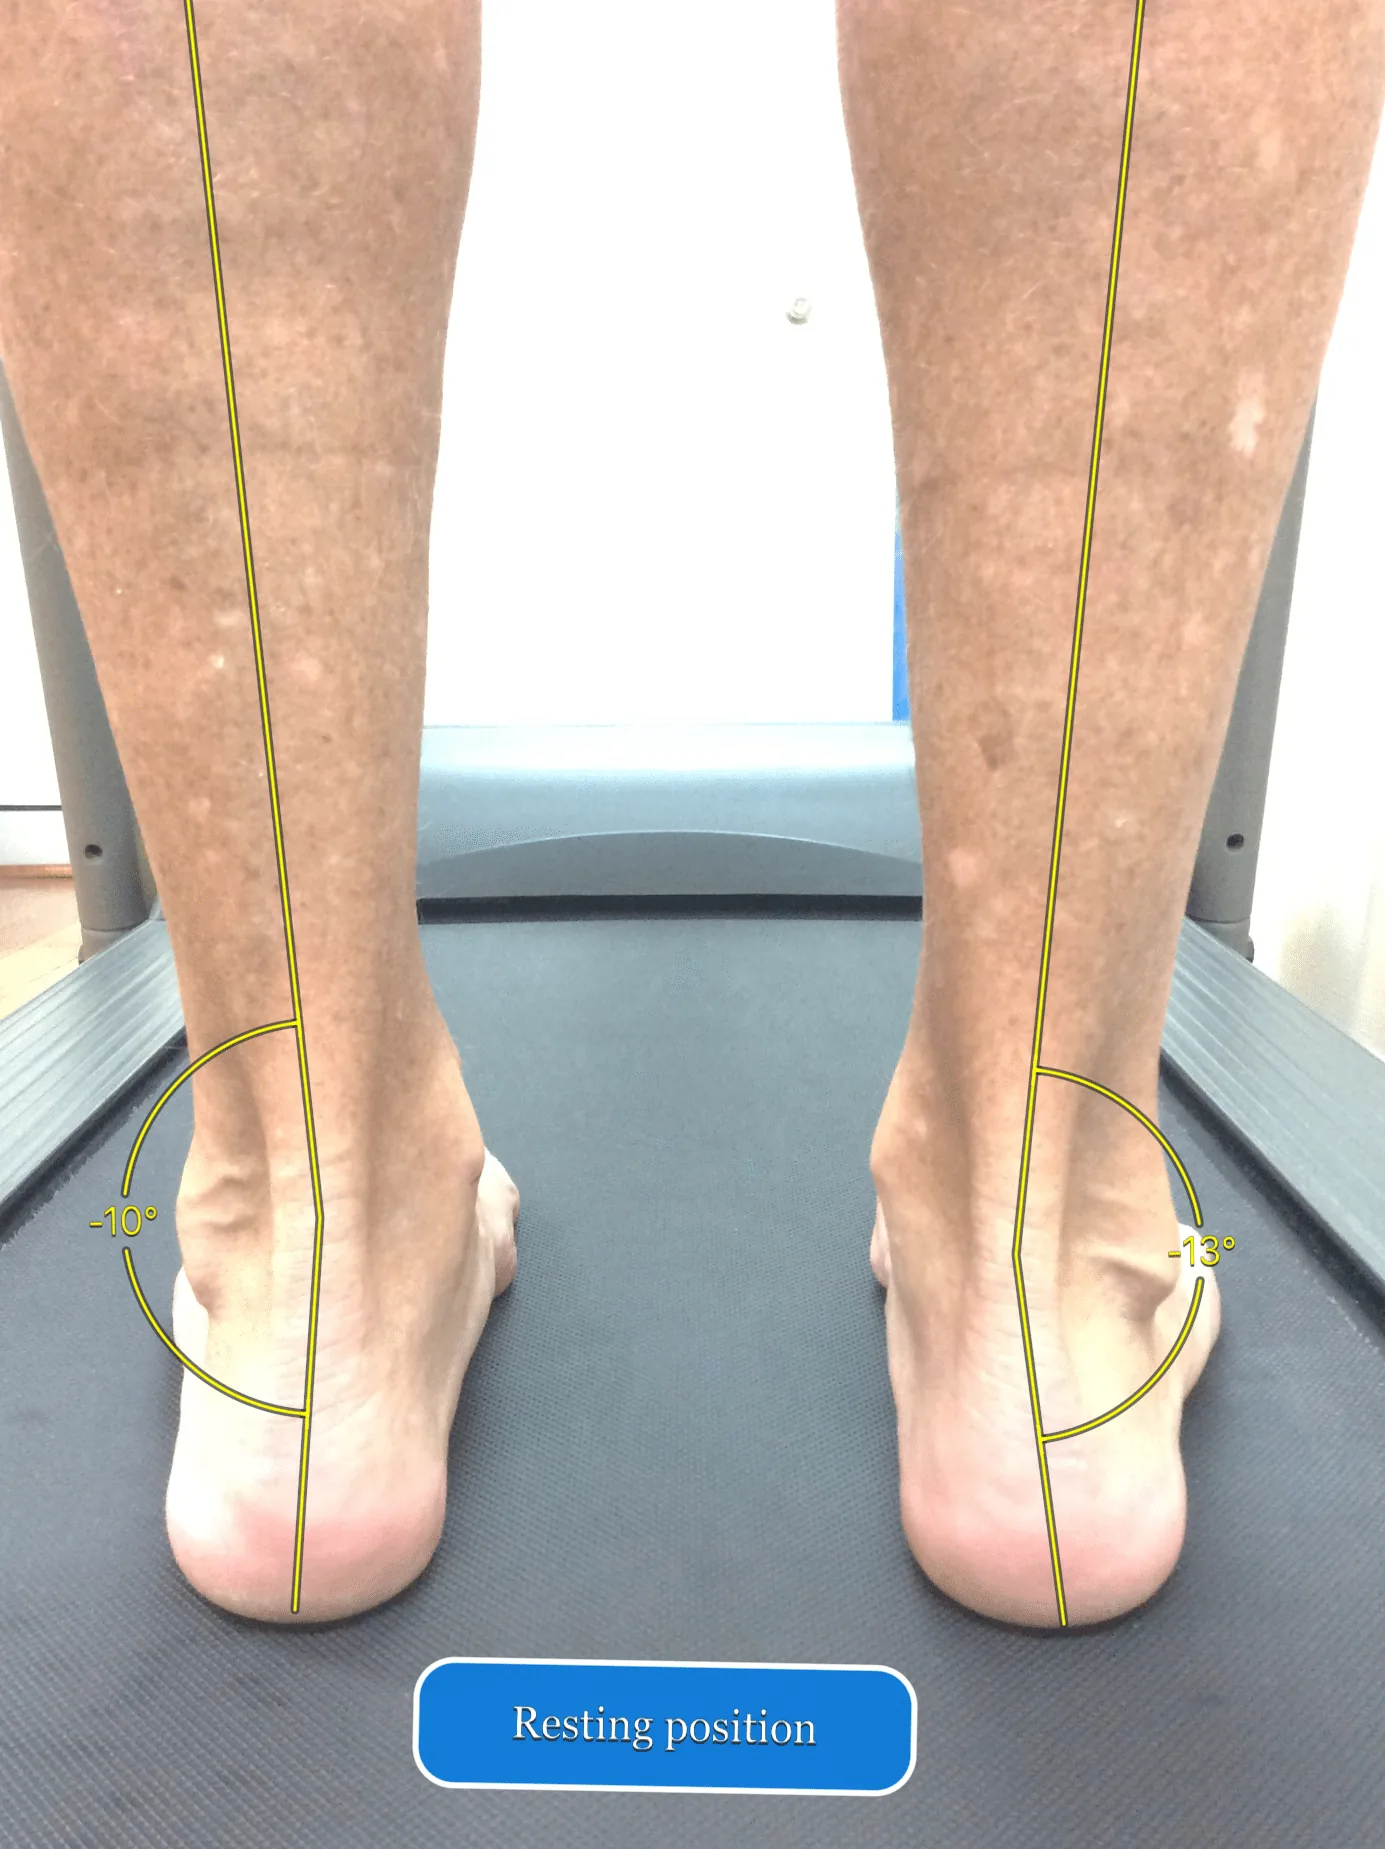





Why it builds with training
The strain is repetitive, so it gets worse as training volume and intensity go up, because the same foot movement repeats with every step.
Pain along the shin that comes on with activity, usually running, and settles with rest.
Trusted by patients from Sydney to Narrabri


If this sounds like your pain, there is a structural reason for it. The assessment is what finds it.
Shin pain usually reflects how load is being transmitted up from the foot. A sudden increase in training, a change of surface, worn footwear or the way the foot rolls through stance can all concentrate stress along the tibia.
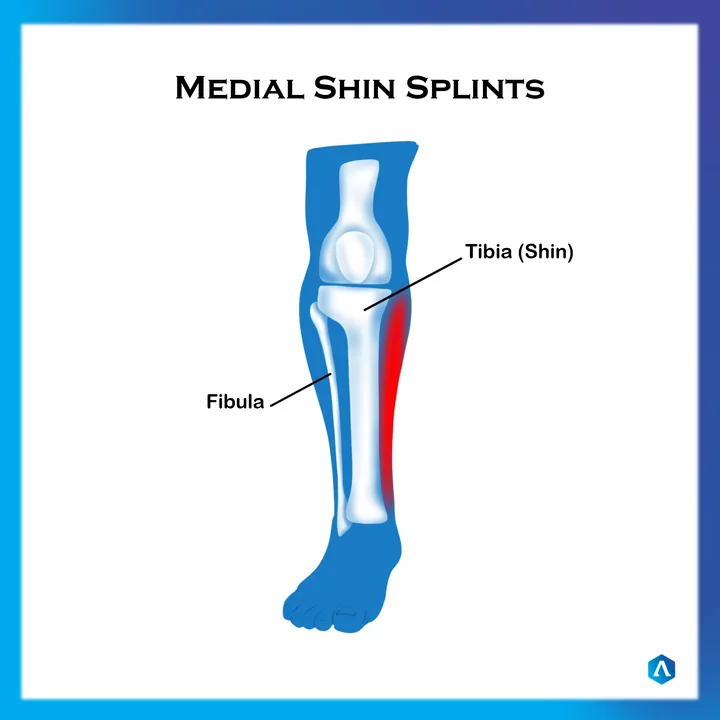
There are three types of shin splints. Each is named for the part of the shin that hurts, and each is linked to a different muscle and a different way the foot moves.
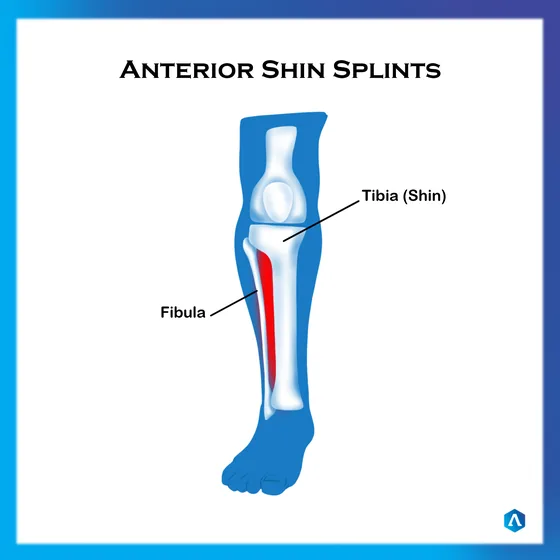
Three types of shin splints
The arch drops and the foot lengthens, stretching the tibialis posterior muscle until it develops tiny tears.
The foot lands on its outer edge, then snaps inwards. The sudden change strains the tibialis anterior muscle at the front.
The foot stays rolled out through the whole step, straining the peroneal muscles on the outside of the leg.
The strain is repetitive, so it gets worse as training volume and intensity go up, because the same foot movement repeats with every step.
An inner-edge type usually needs the rolling-in controlled. Front and outer types need the forefoot corrected so the foot stops landing on its outer edge.
Orthotics, dry needling, shockwave, manipulation and massage.
Shin Splints is diagnosed with the Najjarine Biomechanical Assessment, so treatment is prescribed against a finding rather than a symptom.

We assess your gait under load, because shin pain appears with activity rather than at rest.
We identify what is concentrating the stress and explain what we found.
Treatment addresses the mechanics and the training load together, since changing one without the other usually brings it back.
All ten treatments, starting with those most often used for shin splints. Which you need is decided at the assessment; most plans combine more than one.

Running injuries, return to sport, and footwear that matches your gait.
Read more
Prescribed devices that change how your foot meets the ground. Manufactured on site at our Kirrawee head office.
Read more
Fine needles inserted into trigger points to break down restrictive tissue.
Read more
Hands-on work addressing restrictions across the foot’s 26 bones.
Read more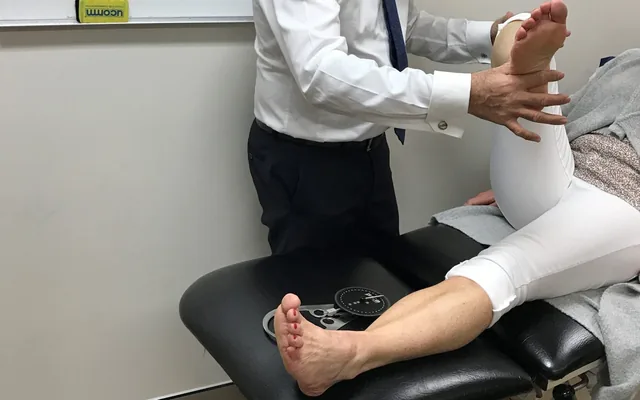
A full lower limb assessment from the feet up. It is the foundation of every treatment plan we prescribe.
Read more
Pigeon toe, flat feet and growing pains, assessed while the foot is still developing.
Read more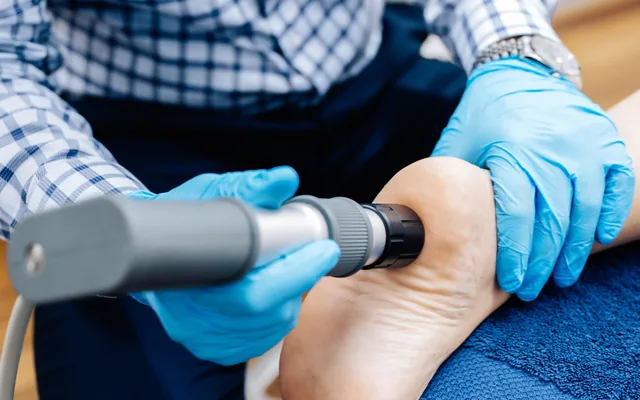
Acoustic waves using kinetic energy to stimulate repair in tendon and soft tissue. We use it most often for persistent heel pain and Achilles pain.
Read more
Routine care including ingrown toenails, corns and calluses.
Read more
Therapeutic support to offload tissue while it recovers.
Read more
Injectable therapy to stimulate a repair response. Paired with prolotherapy.
Read moreEvery clinic books into its own diary. Choose the one nearest you.

Turned out it was my shoes and my training jump together, not one or the other.
Modified my running rather than stopping it. Back to full distance now.
Checked for a stress fracture properly before treating it as shin splints.
They can feel similar. One important difference is whether the tenderness is spread along the bone or sits at one point. If a fracture is suspected we will say so and arrange imaging.
Often in a modified form. Your podiatrist will set out what to change rather than simply stopping you.
Sometimes shoes are part of it and sometimes they are not. Bring the ones you train in to the appointment.
That depends on how long you have trained through it. You will get a realistic timeframe at the assessment.
No. You can book directly.
Treating lower limb pain since 1990
Choose your clinic and book straight into its diary, or call and we will point you to the right practitioner.
