







Why the first steps hurt most
People often describe it as a hot, sharp pain through the heel when they get out of bed, taking 5–10 minutes to ease. It returns after sitting, and burns after a long day standing.
Pain under or behind the heel, most often worst with the first few steps in the morning. It is the single most common problem we see.
Trusted by patients from Sydney to Narrabri


If this sounds like your pain, there is a structural reason for it. The assessment is what finds it.
Most heel pain comes from pronation — the foot rolling in too far. As the arch drops, the foot lengthens and the plantar fascia is elongated, and that repeated stretching causes micro-tears at the base of the heel, where the fascia attaches. A heel spur seen on an X-ray is frequently a result of that loading rather than the cause of the pain.
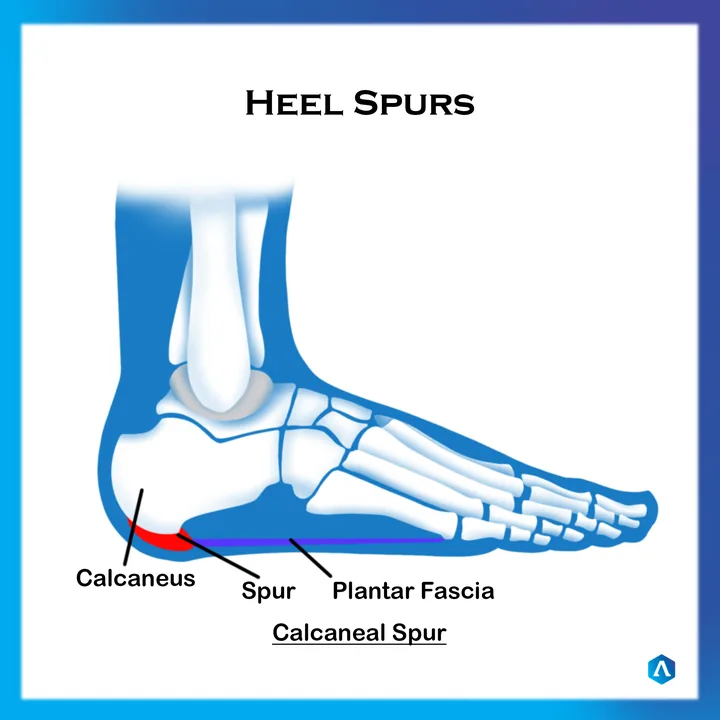
Most heel pain comes from the thick band of tissue under the foot (the plantar fascia) pulling where it attaches to the heel bone. Where on the heel it hurts is a clue to how your foot is moving.
Where it hurts points to why
Linked with the foot rolling inwards too far (over-pronation), which stretches the inner edge of the fascia.
The foot lands on its outer edge, then rolls in. The heel becomes a pivot point for both movements.
Linked with the foot rolling outwards (supination), loading the outer attachment.
People often describe it as a hot, sharp pain through the heel when they get out of bed, taking 5–10 minutes to ease. It returns after sitting, and burns after a long day standing.
Two people can both be told they have plantar fasciitis for opposite reasons: one whose longer leg rolls in to level up with the shorter one, another whose foot rolls out. The treatment is different for each, which is why the assessment comes first.
Orthotics with additions, strapping, massage and foot adjustments, shockwave, dry needling and injection therapy, each aimed at the area that hurts.
Heel Pain is diagnosed with the Najjarine Biomechanical Assessment, so treatment is prescribed against a finding rather than a symptom.

We assess how you stand, walk and load rather than only pressing the sore spot, because the heel is usually where the pain shows up and not where it starts.
We identify what is overloading the tissue — alignment, footwear, activity, or the way the leg above the foot is working — and explain what we found.
Treatment is then prescribed against that finding, which is why two people with the same heel pain can leave with different plans.
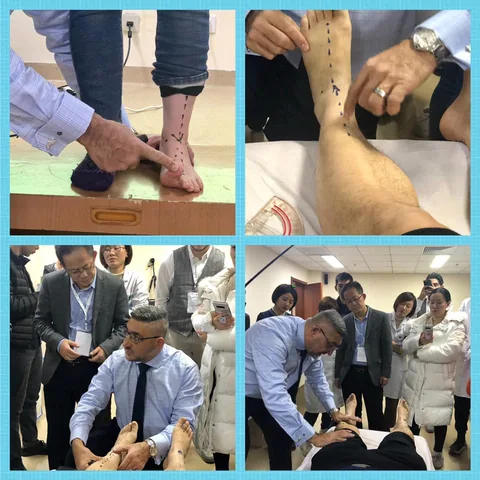
All ten treatments, starting with those most often used for heel pain. Which you need is decided at the assessment; most plans combine more than one.
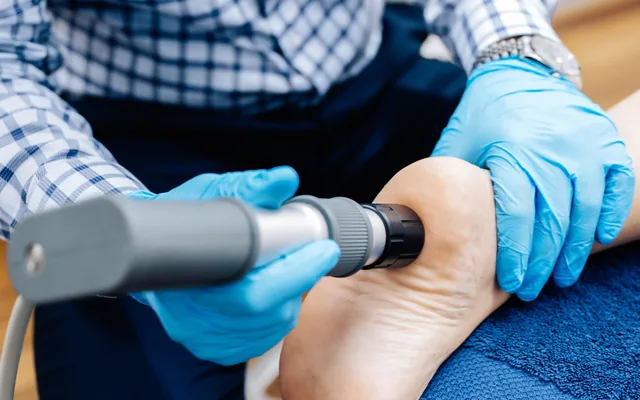
Acoustic waves using kinetic energy to stimulate repair in tendon and soft tissue. We use it most often for persistent heel pain and Achilles pain.
Read more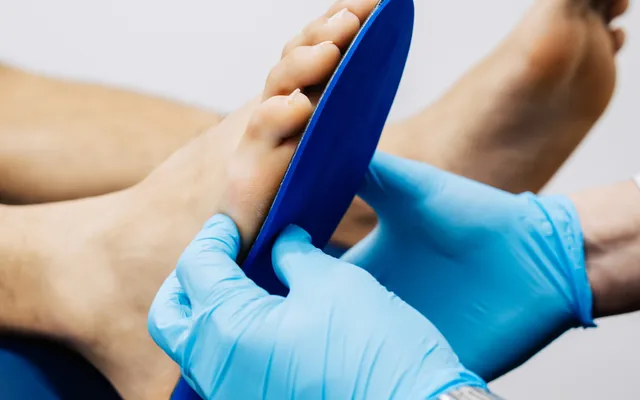
Prescribed devices that change how your foot meets the ground. Manufactured on site at our Kirrawee head office.
Read more
Therapeutic support to offload tissue while it recovers.
Read more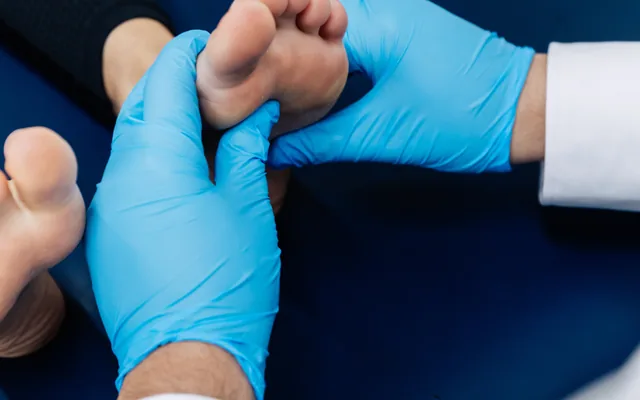
Hands-on work addressing restrictions across the foot’s 26 bones.
Read more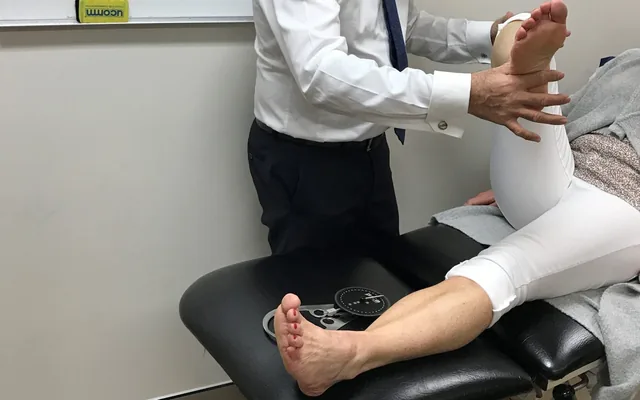
A full lower limb assessment from the feet up. It is the foundation of every treatment plan we prescribe.
Read more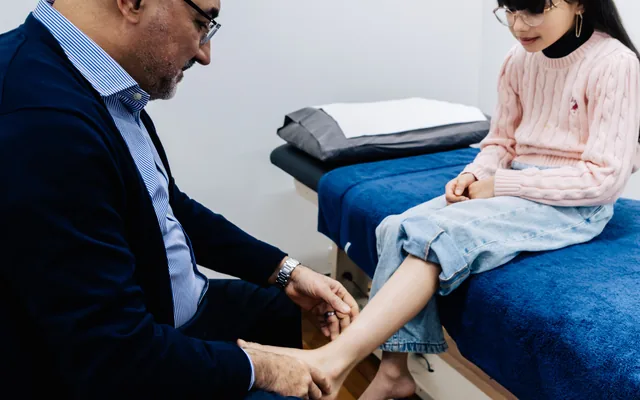
Pigeon toe, flat feet and growing pains, assessed while the foot is still developing.
Read more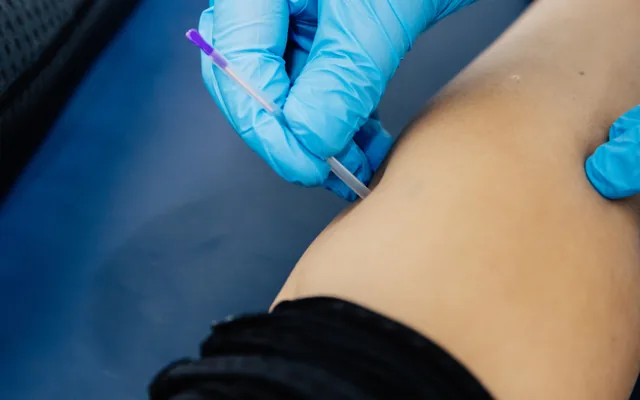
Fine needles inserted into trigger points to break down restrictive tissue.
Read more
Running injuries, return to sport, and footwear that matches your gait.
Read more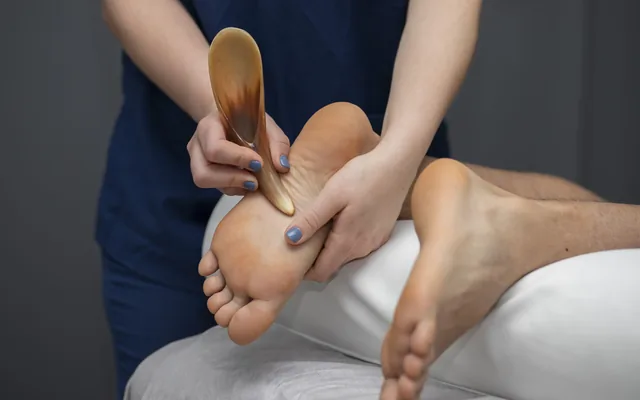
Routine care including ingrown toenails, corns and calluses.
Read more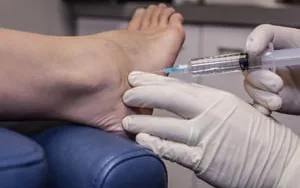
Injectable therapy to stimulate a repair response. Paired with prolotherapy.
Read moreEvery clinic books into its own diary. Choose the one nearest you.

Six months of heel pain and the first appointment was the first time anyone explained what was actually causing it.
Walked out with a plan rather than a guess. The first-step pain was the thing I could never describe properly and they knew exactly what I meant.
Treated the loading rather than just the sore spot, which is why it has stayed away this time.
The tissue under the heel shortens overnight and is loaded suddenly when you stand. That first-step pain is one of the most recognisable features of the problem and is part of what the assessment asks about.
Often not. Spurs show up on X-rays of people with no pain at all, and plenty of people with heel pain have no spur. The assessment looks at loading rather than at the spur alone.
That depends on how long it has been there and what is causing it. Your podiatrist will give you a realistic timeframe at the assessment rather than a standard answer.
Rest alone often helps while you are resting and returns when you go back to normal, because it does not change what caused the overload. That cause is what the assessment is aimed at.
No. Podiatry is a primary contact profession in Australia, so you can book directly.
Treating lower limb pain since 1990
Choose your clinic and book straight into its diary, or call and we will point you to the right practitioner.
