







Turnout from the hip, not the foot
In dancers, forcing turnout from the knee or foot, rather than the hip, can lead to knee, groin, lower back and stomach pain over time.
Out-toeing in children, where the feet point outwards when walking. Assessed the same way as in-toeing.
Trusted by patients from Sydney to Narrabri


If this sounds like your pain, there is a structural reason for it. The assessment is what finds it.
Like in-toeing, out-toeing can originate at the foot, the shin or the hip. Some is expected at particular ages and resolves with growth. What matters is whether it is within the expected range for your child and whether it is causing symptoms.

Out-toeing often comes from the shin bone being twisted outwards, called external tibial torsion. Like pigeon toe, it is often inherited.

The measurements behind it
Some outward turn is healthy. Well beyond that range, the foot points out from the knee down.
Tight groin and hip-flexor muscles show the body is compensating for an outward-turned shin.
Checked alongside the shin, because the two affect each other.
In dancers, forcing turnout from the knee or foot, rather than the hip, can lead to knee, groin, lower back and stomach pain over time.
An outward-turned shin compensated by tight groin muscles twists the knee. That adds to the pull on the growing area below the kneecap in active teenagers.
Stretches, in-toe gait-plate orthotics to guide an outward-turned shin, and re-measuring every few months. See children’s podiatry.
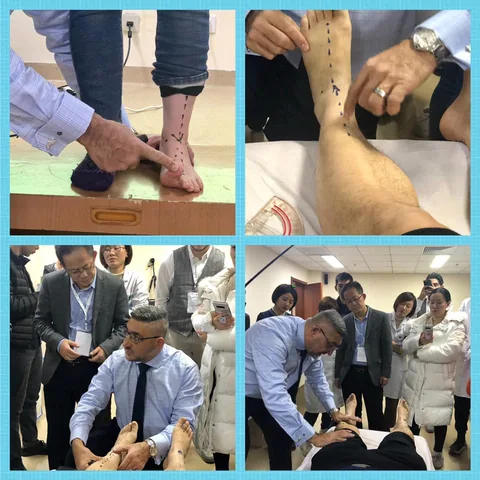
Out Toe is diagnosed with the Najjarine Biomechanical Assessment, so treatment is prescribed against a finding rather than a symptom.

We assess how your child stands, walks and runs against what is expected for their age.
We identify which level the rotation is coming from and explain what we found.
Where nothing needs doing we say so and set a review. Where it does, treatment is staged around growth.
All ten treatments, starting with those most often used for out toe. Which you need is decided at the assessment; most plans combine more than one.
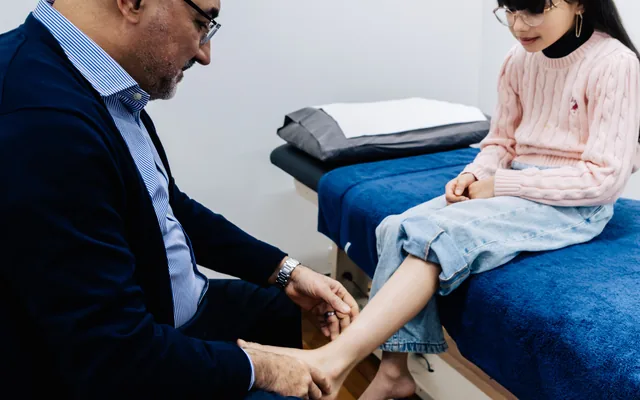
Pigeon toe, flat feet and growing pains, assessed while the foot is still developing.
Read more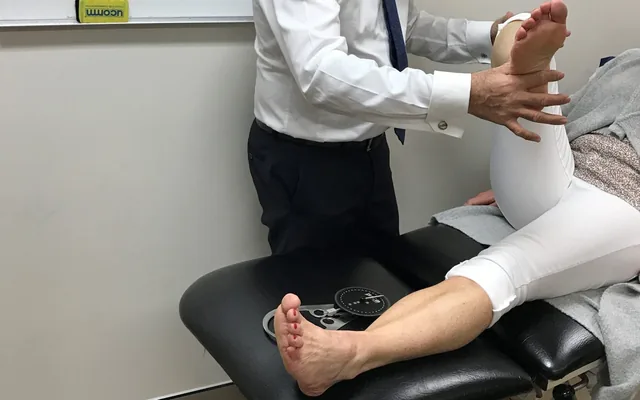
A full lower limb assessment from the feet up. It is the foundation of every treatment plan we prescribe.
Read more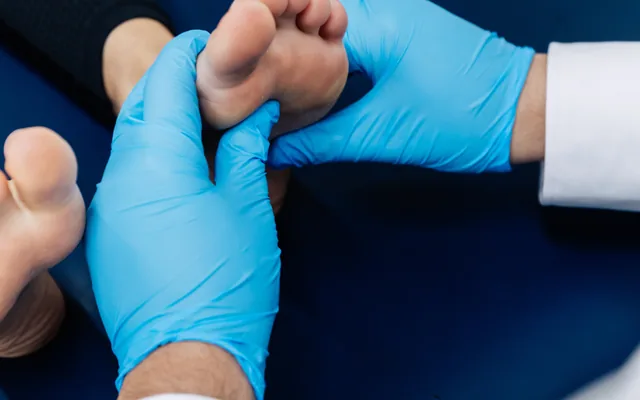
Hands-on work addressing restrictions across the foot’s 26 bones.
Read more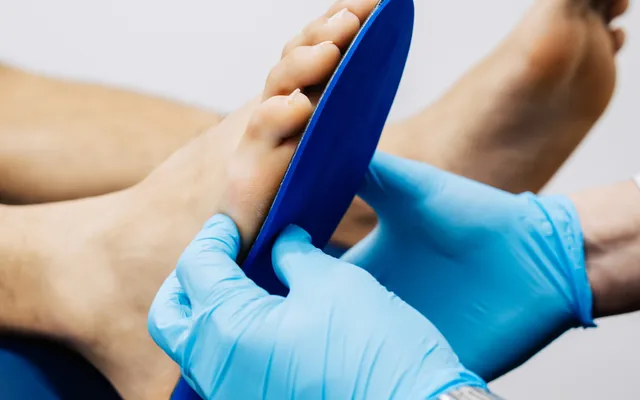
Prescribed devices that change how your foot meets the ground. Manufactured on site at our Kirrawee head office.
Read more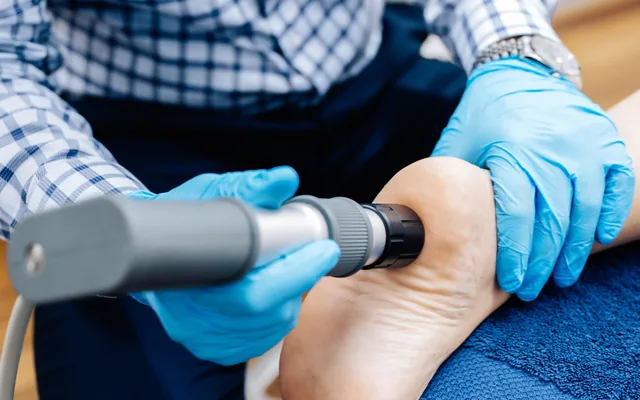
Acoustic waves using kinetic energy to stimulate repair in tendon and soft tissue. We use it most often for persistent heel pain and Achilles pain.
Read more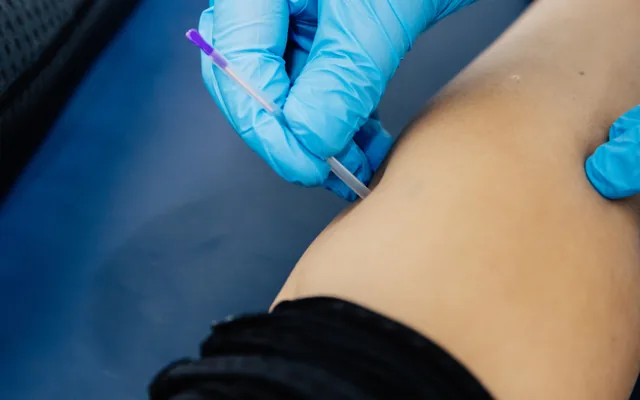
Fine needles inserted into trigger points to break down restrictive tissue.
Read more
Running injuries, return to sport, and footwear that matches your gait.
Read more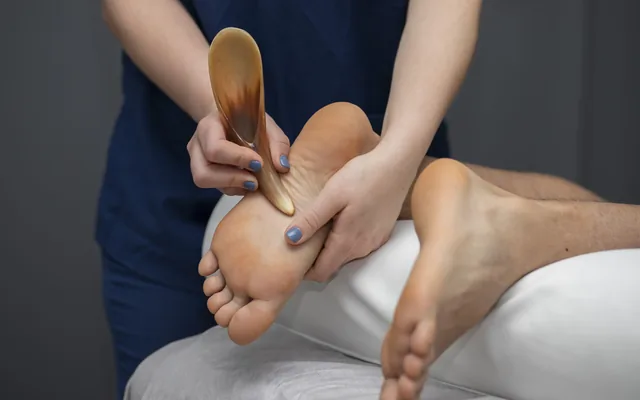
Routine care including ingrown toenails, corns and calluses.
Read more
Therapeutic support to offload tissue while it recovers.
Read more
Injectable therapy to stimulate a repair response. Paired with prolotherapy.
Read moreEvery clinic books into its own diary. Choose the one nearest you.

Reassuring and thorough. We knew where we stood by the end of the appointment.
Took the time to show us what they were seeing as our son walked.
Honest about what did and did not need doing.
Neither is automatically worse. Both are assessed the same way.
It can affect comfort and efficiency. Whether it is worth addressing is what the assessment establishes.
There is no fixed age. If you have noticed it or your child is complaining, that is the time.
Some rotational patterns do. Your podiatrist will ask about family history as part of the assessment.
No. You can book directly.
Treating lower limb pain since 1990
Choose your clinic and book straight into its diary, or call and we will point you to the right practitioner.
